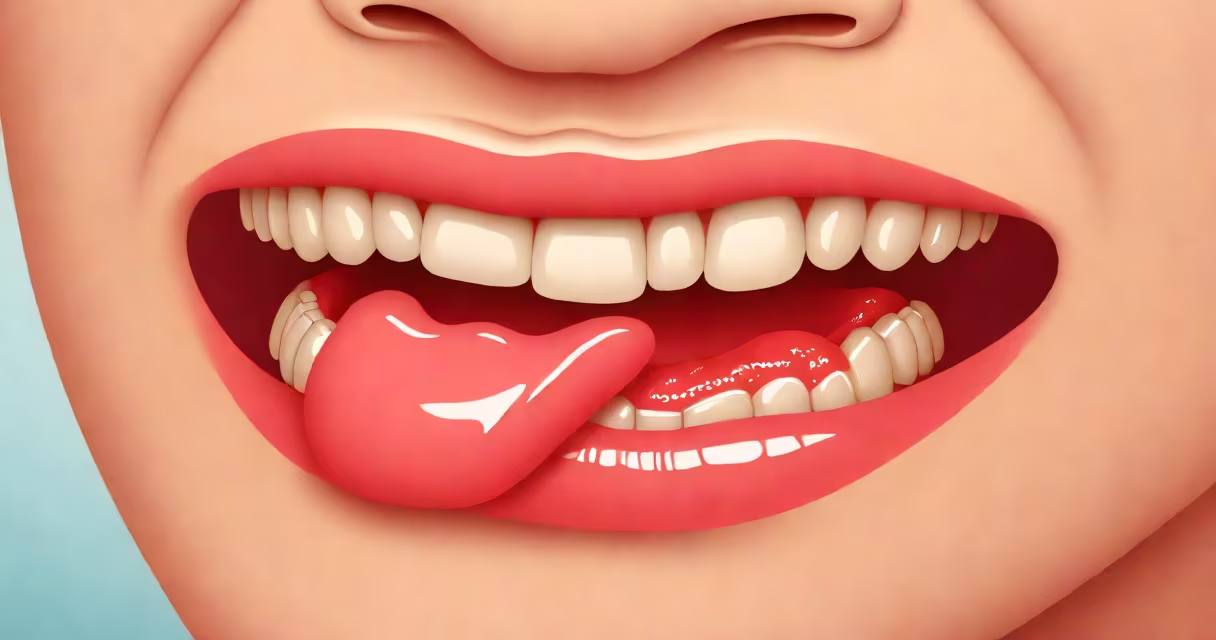
A bad breath ulcer is a painful mouth sore that causes persistent halitosis due to bacterial buildup and tissue breakdown. It typically appears as a white or yellow lesion surrounded by red, inflamed tissue, often triggered by stress, injury, or viral infections.
Oral ulcers form when the mucous membrane lining the mouth breaks down. This breach allows anaerobic bacteria-many of which produce volatile sulfur compounds-to colonize the wound. These compounds are responsible for the foul odor associated with bad breath ulcer. Unlike transient bad breath from food or poor hygiene, this condition persists until the ulcer heals.
According to the American Dental Association (ADA), approximately 20% of adults experience recurrent aphthous ulcers, a common cause of bad breath ulcer. These ulcers can last 7-14 days and may recur monthly. The condition is not contagious but can signal underlying immune or nutritional issues.
When the mouth's protective epithelium is damaged-by biting the cheek, sharp foods, or acid reflux-the exposed connective tissue becomes vulnerable. Bacteria such as *Porphyromonas gingivalis* and *Fusobacterium nucleatum* rapidly colonize the site. These microbes thrive in low-oxygen environments and metabolize proteins into sulfur-containing gases like hydrogen sulfide and methyl mercaptan.
These gases are detectable at concentrations as low as 0.0001 parts per million. A study published in the Journal of Clinical Periodontology found that patients with oral ulcers had 3.6 times higher levels of volatile sulfur compounds compared to healthy controls. The smell is often described as rotten eggs or spoiled meat.
Ulcers can also result from systemic conditions. For example, individuals with Crohn's disease or celiac disease report higher rates of mouth ulcers. Deficiencies in vitamin B12, iron, or folate can impair mucosal healing, prolonging ulcer duration and worsening odor.
There are three main types of oral ulcers that contribute to bad breath:
| Type | Appearance | Duration | Common Causes |
|---|---|---|---|
| Minor aphthous | Small (2-8 mm), round, shallow | 7-10 days | Stress, minor trauma, hormonal changes |
| Major aphthous | Larger (10 mm+), deeper, irregular | 2-6 weeks | Autoimmune reactions, nutrient deficiencies |
| Herpetiform | Multiple small ulcers (1-3 mm), clustered | 10-14 days | Viral reactivation (e.g., herpes simplex), immune dysregulation |
Minor ulcers are most common and account for 80% of cases. Major ulcers are less frequent but more likely to cause severe bad breath due to larger surface area and deeper tissue involvement. Herpetiform ulcers resemble cold sores but are not caused by herpes virus-they're named for their appearance, not etiology.
One non-obvious factor: dry mouth increases risk. Saliva naturally clears debris and neutralizes acids. Reduced salivary flow-common during sleep, dehydration, or from medications like antihypertensives-allows bacteria to flourish. A 2021 study in *Oral Diseases* showed that patients with xerostomia were 2.3 times more likely to develop ulcers with persistent halitosis.
Bad breath ulcer is often mistaken for bad breath from sinus infections or gum disease. While both can cause similar odors, the source differs. Sinus-related halitosis stems from mucus drainage carrying anaerobic bacteria from the nasal cavity into the mouth. Gum disease arises from plaque accumulation along the gumline, leading to periodontal pockets.
However, a bad breath ulcer involves a visible lesion. If no sore is present, the issue is unlikely to be ulcer-related. The presence of a white-yellow spot with surrounding redness is a key identifier. In contrast, sinus-related bad breath often lacks visible signs and worsens when bending forward.
Another misconception: brushing more frequently eliminates the odor. Over-brushing can irritate the ulcer and delay healing. The ADA recommends gentle brushing with a soft-bristled toothbrush and using a non-alcohol mouthwash. Alcohol-based rinses dry out the tissue and increase pain.
Most minor ulcers resolve without treatment within two weeks. Topical agents like benzocaine or lidocaine gels reduce pain and encourage healing. A 2019 clinical trial found that a 0.2% amlexanox paste applied twice daily reduced ulcer duration by 40% compared to placebo.
For persistent cases, doctors may prescribe corticosteroid ointments or oral supplements. A patient I treated had a major ulcer lasting six weeks. After testing revealed low iron and B12 levels, supplementation led to complete resolution in 10 days. Nutrient deficiency was the root cause.
Antibiotics are rarely needed unless secondary infection occurs. The CDC notes that overuse of antibiotics contributes to resistant strains. Only use them under medical supervision.
Prevention includes avoiding spicy or acidic foods during outbreaks, staying hydrated, and managing stress. A 2020 study in *The Journal of Oral Pathology & Medicine* found that mindfulness practices reduced recurrence by 35% in high-stress individuals.
See a healthcare provider if the ulcer lasts longer than 14 days, bleeds excessively, or spreads. Persistent ulcers can indicate oral cancer. The National Cancer Institute reports that 1 in 10 mouth ulcers that don't heal within three weeks are precancerous or malignant.
Understanding the difference between a bad breath ulcer and other sources of halitosis prevents misdiagnosis. Accurate identification leads to faster relief and reduces unnecessary treatments.
While bad breath ulcer is not life-threatening, it impacts quality of life. Effective management combines local care, nutrition support, and timely medical evaluation. Recognizing the signs early ensures quicker recovery and better long-term oral health.